Prescribing home exercises: how to design a program patients actually do
Whether a home program has an effect depends to a large extent on whether the patient does it. Below are six points that help. For each one, it says what has been studied and what comes from clinical experience.
1. Prescribe fewer exercises than you think
The optimal number of exercises has hardly been studied. Henry et al. (1999) gave 15 community-dwelling adults over 65 either two, five or eight strengthening exercises. After 7 to 10 days, the two-exercise group performed them better than the eight-exercise group; the five-exercise group didn't differ from either. Their own exercise logs showed no difference in how often they exercised. It's a small study, but it points in one direction.
Three to five exercises per program is a common rule of thumb. It comes from practice, not from a trial. A split that often works:
- two exercises that target the primary goal
- one or two supporting exercises
- anything else you'd like to add waits for a later visit
2. Set realistic parameters
Reps, sets, rest and load determine the training stimulus, but also whether the exercise fits into someone's day.
Start below the patient's load capacity. More pain during exercise is associated with poorer adherence (Jack et al., 2010), and a program that loads to the maximum in week one makes that pain more likely.
Then progress gradually. Self-efficacy comes up in several reviews as a factor in adherence (Jack et al., 2010; Essery et al., 2017; Chester et al., 2023). Noticing that an exercise is getting easier or can be loaded more contributes to it.
Agree on how the patient handles pain. Without an agreement, one patient stops at the slightest twinge and another pushes straight through. Agree on a limit on a 0 to 10 scale: if pain goes above it, the patient does fewer reps rather than stopping altogether. Also agree on when the patient should contact you, for example if pain hasn't settled by the next day or new symptoms appear.
Make frequency concrete. "A few times a day" is hard to plan; "twice a day, five days a week" isn't.
3. Add context to each exercise
In a scoping review of 28 studies, Chester et al. (2023) mapped thirteen modifiable determinants of home exercise adherence. Self-efficacy, social support and whether the patient sees the value of the exercise came up most often. You can influence that last one directly by briefly noting for each exercise:
- Goal. "Strengthens the muscles that stabilise your hip."
- Frequency. "Twice a day, five days a week."
- When to scale back. "Fewer reps if pain rises above the agreed limit."
One or two sentences per exercise is enough.
4. Show the exercise, and send it home with them
How you hand over the program partly determines what the patient still knows at home.
- Demonstrate and have them repeat it, or use video. Reo & Mercer (2004) taught 40 healthy adults five shoulder exercises by live demonstration, video or a handout alone. The handout-only group made more than twice as many errors as the average of the live and video groups. Live and video didn't differ, so a video of each exercise is a good addition for home.
- Photo with text. Useful as a reminder, especially for a patient who already knows the exercise. It doesn't show movement or tempo.
- Text only. Enough for returning patients who already perform the exercise well.
- Verbal only. According to a widely cited review, patients immediately forget 40 to 80 percent of the medical information they're given (Kessels, 2003). So always give them something to take home.
Hand over the program during the visit, not afterwards. Have the patient do each exercise once while you watch, and ask whether they can do it at home with the space, equipment and time they have. That way you hear about practical obstacles before they leave.
5. Schedule follow-up from the start
- Book the next appointment before the patient leaves the clinic, rather than leaving it to them to call back.
- A brief check-in in between can help, for example a message a few days before the next appointment asking whether the program is going OK.
- At the follow-up, ask exercise by exercise what did and didn't get done. "How's it going?" usually gets a "fine", even when half of it was skipped.
There is research supporting this kind of extra support. In the review by Lang et al. (2022), seven of ten RCTs found better adherence when a home program was supplemented with a digital intervention, such as text-message reminders, an app or videos; the longer-term effect was less clear. In a meta-analysis of home-based video exercise programs in adults over 65, mostly supervised online classes, average attendance was 85 percent and 91 percent of participants stayed in the program. Without live contact with an instructor, attendance was lower (Rihova et al., 2024).
6. Adjust the program based on what happened
At the follow-up you want to know what the patient did and what it achieved. Four patterns that come up often:
- Not done, no progress: find out why and simplify (fewer exercises, lower load, a time of day that fits better).
- Done, no progress: look at dosage and selection. The load may be too low, the period still too short, or the exercise may not suit the problem. If progress still doesn't come, test your working hypothesis too.
- Done, progress made: increase the load or add something.
- The patient asks for more: make room for it.

Don't hold on to a program just because that's what you agreed. It's a working document.
The thread running through all of it
Patient motivation plays a role (Essery et al., 2017), but part of what determines adherence is up to you: how much you prescribe, how clearly you explain and hand it over, and whether you follow up. Prescribe less than you planned, have the patient do each exercise once, and schedule a check within two weeks.
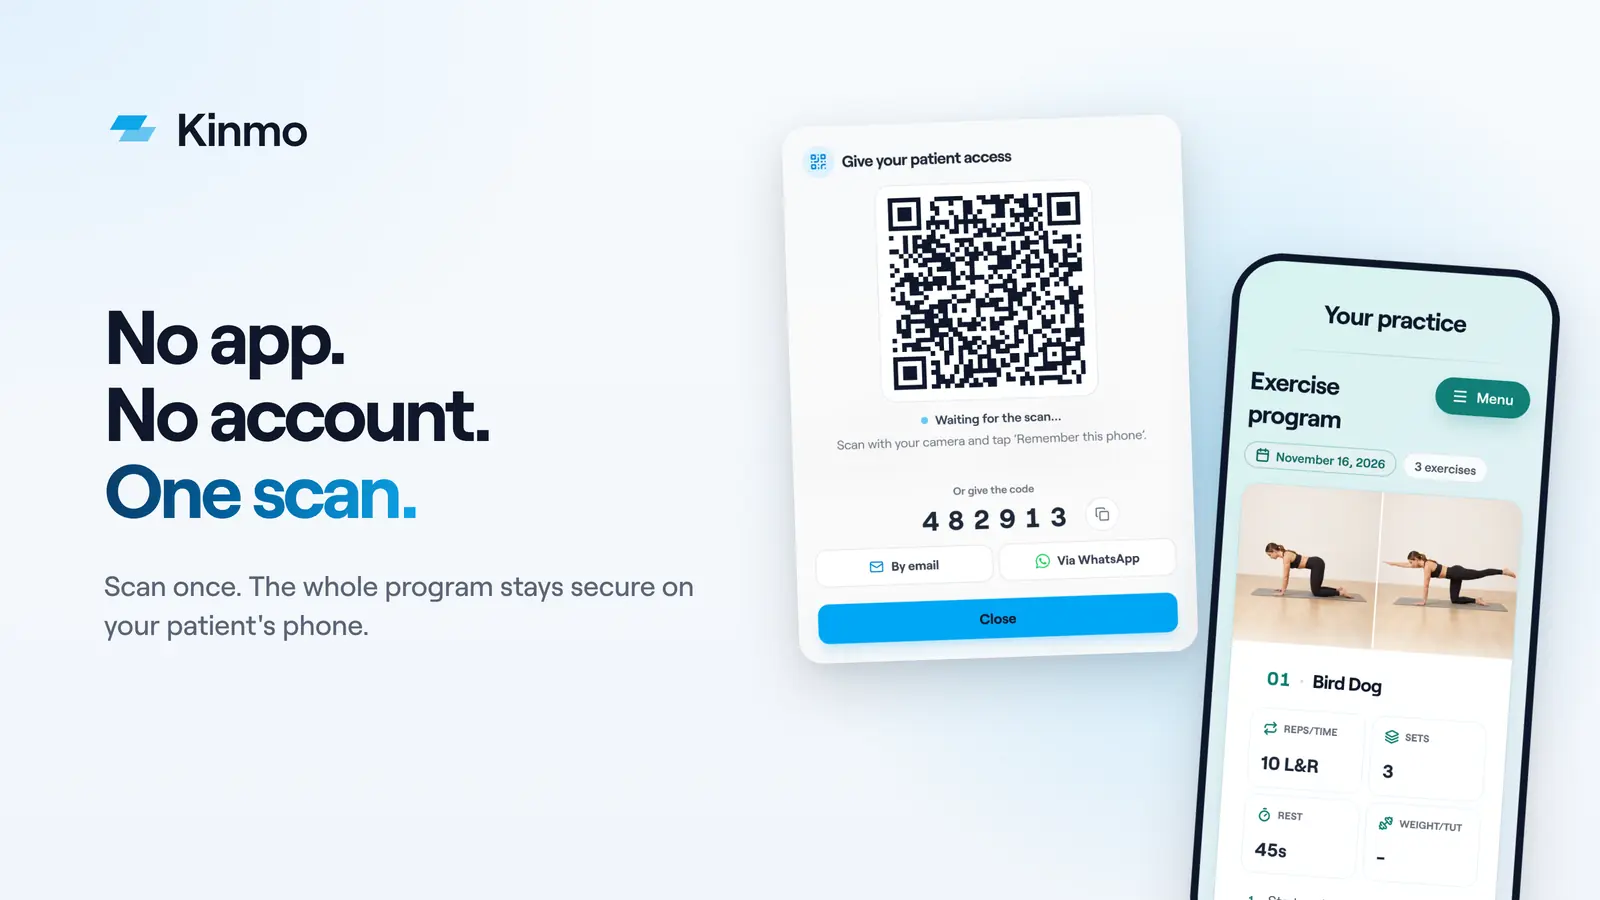
Kinmo is our own product and helps with prescribing and handing over: you put together a program with a photo or video and instructions for each exercise, and the patient opens it from a single link without an app or account and can add the exercise days to their own calendar. Follow-up is still yours to do in the visit. If you want patients to tick off exercises or enter a pain score, you need a tool that keeps patient data. Kinmo deliberately doesn't.
Sources
- Henry, K.D., Rosemond, C. & Eckert, L.B. (1999). Effect of number of home exercises on compliance and performance in adults over 65 years of age. Physical Therapy, 79(3), 270-277. PMID 10078770
- Jack, K., McLean, S.M., Moffett, J.K. & Gardiner, E. (2010). Barriers to treatment adherence in physiotherapy outpatient clinics: a systematic review. Manual Therapy, 15(3), 220-228. PMID 20163979
- Essery, R., Geraghty, A.W.A., Kirby, S. & Yardley, L. (2017). Predictors of adherence to home-based physical therapies: a systematic review. Disability and Rehabilitation, 39(6), 519-534. PMID 27097761
- Chester, R. et al. (2023). Behaviour Change Techniques to promote self-management and home exercise adherence for people attending physiotherapy with musculoskeletal conditions: a scoping review and mapping exercise. Musculoskeletal Science and Practice, 66, 102776. PMID 37301059
- Reo, J.A. & Mercer, V.S. (2004). Effects of live, videotaped, or written instruction on learning an upper-extremity exercise program. Physical Therapy, 84(7), 622-633. PMID 15225081
- Kessels, R.P.C. (2003). Patients' memory for medical information. Journal of the Royal Society of Medicine, 96(5), 219-222. PMID 12724430
- Rihova, M. et al. (2024). Adherence and Retention Rates to Home-Based Video Exercise Programs in Older Adults: Systematic Review and Meta-Analysis. Telemedicine and e-Health, 30(11), 2649-2661. PMID 39072676
- Lang, S., McLelland, C., MacDonald, D. & Hamilton, D.F. (2022). Do digital interventions increase adherence to home exercise rehabilitation? A systematic review of randomised controlled trials. Archives of Physiotherapy, 12(1), 24. PMID 36184611